
Evaluation and Treatment of Constipation
Marisa Battistella, BScPhm, Pharm D, Education Coordinator & Hemodialysis Pharmacist, Pharmacy Department, University Health Network, Toronto, ON.
Shabbir M.H. Alibhai, MD, MSc, FRCP(C), Staff Physician, University Health Network, Toronto, ON.
Constipation is a common symptom in patients of all ages, but its occurrence is highest among persons 65 years of age or older.1,2 Constipation has been shown to diminish both quality of life and feeling of well-being.3-5 Although constipation can have many causes, it is most often functional or idiopathic.5,6 Furthermore, constipation can lead to serious complications such as malnutrition, fecal impaction, fecal incontinence, colonic dilation and even perforation of the colon.7
Definition
Constipation has different meanings to patients and physicians. A patient's perception of constipation may include not only the objective observation of infrequent bowel movements but also subjective complaints of straining with defecation, incomplete evacuation, abdominal bloating or pain, hard or small stools or a need for digital manipulation to enable defecation. Because the definition of constipation can be subjective, an international committee has recommended an operational definition of chronic functional constipation in adults.8 The Rome II criteria for defining chronic functional constipation in adults are as follows:
Two or more of the following for at least 12 weeks in the preceding 12 months:
- straining in more than 25% of defecations
- lumpy or hard stools in more than 25% of defecations
- sensation of incomplete evacuation in more than 25% of defecations
- manual maneuvers (e.g., digital evacuation, support of the pelvic floor) to facilitate more than 25% of defecations
- fewer than three defecations per week
- loose stools are not present and there are insufficient criteria for the diagnosis of irritable bowel syndrome.8
Epidemiology
A survey of Canadians 18 years or older estimated the prevalence of functional constipation to be 14.9% according to Rome II criteria.9 The rate of constipation for women was close to twice the rate among men. Of all the subjects with Rome II-defined functional constipation, 26.3% reported using prescribed or over-the-counter medication in the past three months for their constipation.9
Pathogenesis
Normal colonic motility combines segmenting contractions that promote mixing of luminal contents, propagating contractions that propel them short distances and high amplitude contractions that transport them long distances.
Although the etiology of constipation is uncertain, it is now known that the frequency of bowel movement is not reduced with normal aging, nor does aging alone seem to slow intestinal transit.10,11
Constipation results from disordered movement through the colon and/or anorectum. It may be due to gastrointestinal motility problems (Table 1),12,13 or it may be secondary to structural, neurological or metabolic abnormalities (Table 2)12,14-18 or drug therapy (Table 3).12
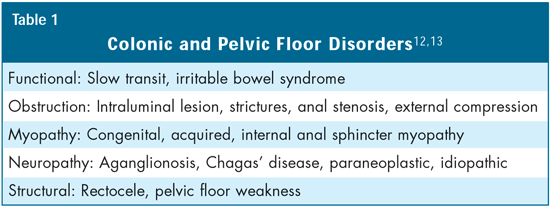
The majority of individuals with constipation do not have an identifiable cause to explain their symptoms. However, it is important to distinguish functional constipation from other disorders that can be associated with altered bowel habits. The history and physical exam frequently provide much of the necessary diagnostic information to determine the cause of constipation. It is particularly important to distinguish recent change in bowel habit (i.e., within the last three to six months) from chronic constipation, as the former is more likely due to one of the causes listed in Tables 1 to 3.

Evaluation
Physical examination
Most chronically constipated individuals do not require an extensive diagnostic evaluation. The initial assessment should incorporate a careful history and examination with an attempt to identify disorders or risk factors that may be associated with constipation. A recent or persistent change of bowel habits should prompt further evaluation for any