
Update on Endocrine Therapy for Postmenopausal Women in Early Breast Cancer
A large proportion of breast cancers in older women have positive hormone receptors. Therefore, these women are eligible to receive adjuvant endocrine therapy to decrease their chance of cancer recurrence. Over the last few years, a new class of endocrine therapy, aromatase inhibitors (AIs), has challenged the place of tamoxifen as the gold standard adjuvant endocrine agent. We will discuss randomized clinical trials comparing tamoxifen to AIs in terms of efficacy and side effects.
Key words: breast cancer, tamoxifen, aromatase inhibitors, side effects, quality of life.
Introduction
Age is a risk factor for breast cancer (BC). Therefore, it is not surprising that more than 50% of all women diagnosed with breast cancer in Canada are age 60 or older and nearly 30% are over 70 years old.1 Among newly diagnosed women, older patients are more likely to have tumours expressing estrogen receptors2-4 and at a higher level than younger patients.3 Over 80% of tumours diagnosed in women older than 65 years of age express estrogen receptors;2,3 therefore, these patients are eligible to receive adjuvant hormonal therapy. We will discuss the indications, benefits, and side effects of hormonal therapy given in the adjuvant setting.
Indications
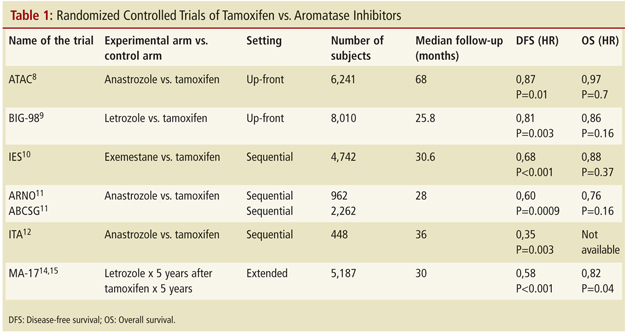
Until recently, tamoxifen was the standard adjuvant endocrine therapy for hormone-sensitive early breast cancer. The addition of five years of tamoxifen reduces recurrence and mortality risks by 47% and 26%, respectively.5 The optimal duration of treatment is usually five years, since longer therapy with tamoxifen does not seem to confer any extra benefits in terms of disease-free survival (DFS).6 The third-generation aromatase inhibitors (AIs) anastrozole, letrozole, and exemestane are highly selective for aromatase and inhibit 97-99% of estrogen synthesis. Their use is restricted to postmenopausal women. In the last few years, results of important trials have challenged the place of tamoxifen as the gold standard for adjuvant therapy in the early stage breast cancer population. Three different ways of using AIs in adjuvant treatment have been compared in randomized clinical trials (RCTs), the results of which are presented below and summarized in Table 1.
Initial therapy
Two RCTs have been conducted comparing upfront AIs to up-front tamoxifen (endocrine therapy was started soon after surgery or completion of chemotherapy, if given). The first published RCT, Arimidex, Tamoxifen, Alone or in Combination (ATAC),7 used three arms: anastrozole, tamoxifen, and a combination of both, and compared the effects of those three arms. As the combination arm showed no efficacy or tolerability benefits compared to the tamoxifen alone arm, this arm was discontinued after the initial analyses. The last analysis,8 completed after 68 months of median follow-up of the two monotherapy arms (6,186 patients) demonstrated a significant advantage of anastrozole over tamoxifen with a 13% improvement in DFS, corresponding to an absolute difference of 3.7% at six years (hazard ratio [HR] 0.87, p=0.013). Even though anastrozole decreased distant recurrences (HR 0.86, p = 0.04), the difference in overall survival (OS) was not statistically significant (p=0.7). The second trial published in this setting is the Breast International Group (BIG) 1-98 trial9 comparing letrozole to tamoxifen. Over 8,000 postmenopausal patients